Anterior hip replacement
A total hip replacement removes the worn ball and socket of an arthritic hip and replaces them with artificial parts. Dr Frank Connon performs routine first-time hip replacements on the Sunshine Coast through the direct anterior approach: a short incision at the front of the hip, with the muscles moved aside rather than cut. Most people are up on their feet within hours and go home after 1 to 2 nights. A hip replacement relieves pain for most people, but the new joint does not feel like a 25-year-old’s.
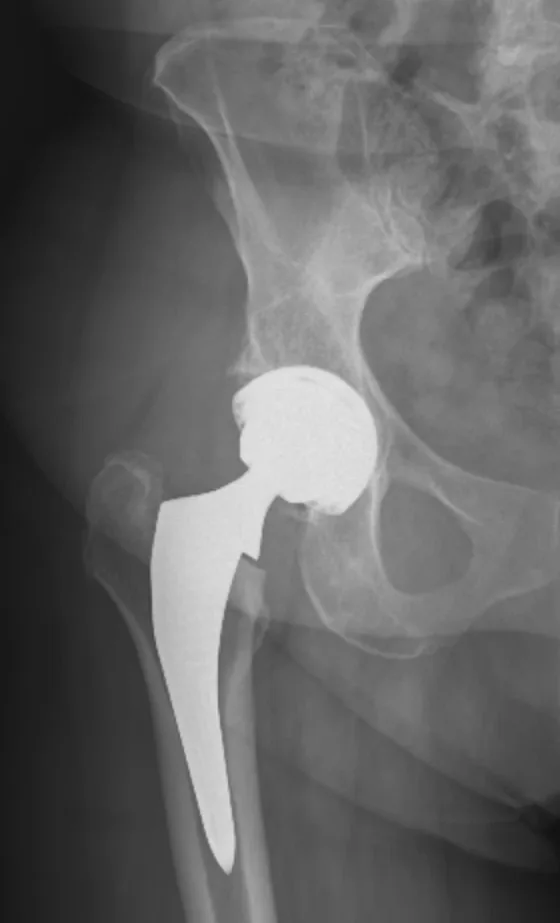
Key facts
- What it is
- A new ball and socket for an arthritic hip, through the direct anterior approach: a short incision at the front of the hip, with the muscles moved aside rather than cut.
- Who it suits
- People whose hip arthritis, clear on X-ray or MRI, is significantly affecting their life despite non-surgical treatment. There is no set age limit.
- Hospital stay
- Usually 1 to 2 nights. Self-funded patients usually go home on the day of surgery or after 1 night, if it is safe for them and they have support at home.
- Back to normal life
- On your feet within hours. Driving at about 2 weeks (left hip, automatic car) or up to 4 weeks (right hip), swimming at about 4 weeks, and surfing from about 12 weeks.
- Cost
- With insurance: Gold hospital cover, or a Silver Plus policy that includes joint replacement. Self-funded: approximately $27,000 to $28,000. You receive a written quote before surgery.
- Where it is done
- On the Sunshine Coast, at Noosa Hospital, Buderim Private Hospital or Sunshine Coast University Private Hospital. Appointments are at our Noosaville and Birtinya rooms.
Is a hip replacement right for you?
A hip replacement may help if hip arthritis is significantly affecting your quality of life, for example through pain or reduced mobility, despite non-surgical treatment. Your X-rays or MRI need to show clear arthritis, and it needs to be what you want. There’s no set age limit.
Dr Connon will talk through what you can expect, the risks, and the alternatives, including waiting. You make the decision together.
Hip replacement is also used for avascular necrosis of the hip and for arthritis caused by hip dysplasia.
What is the direct anterior approach?
“Approach” means the route the surgeon takes to reach the hip joint.
- A short skin incision, usually 8 to 12 cm, is made at the front of the hip. In some people a “bikini” incision, running along the skin crease, is possible.
- The muscles are spread apart, not cut.
- The worn ball and socket are removed. A new socket (cup) is fixed into the pelvis and a stem with a new ball is placed in the thigh bone.
- An X-ray during the operation confirms the position of the implants, and Dr Connon checks the hip’s stability before finishing.
Dr Connon offers the anterior approach for all routine first-time hip replacements.
Anterior vs posterior hip replacement: what’s the difference?
The posterior approach, through the back of the hip, is still the most common approach in Australia. The table sets the two side by side.
| Anterior | Posterior | |
|---|---|---|
| Route to the hip | Through the front of the hip, with the muscles moved aside rather than cut | Through the back of the hip, which requires several muscles to be cut and repaired. Still the most common approach in Australia |
| Early recovery | On average, faster recovery and less pain over roughly the first 6 weeks, in studies of experienced surgeons [1–5] | On average, slower recovery and more pain over roughly the first 6 weeks in the same studies [1–5] |
| Precautions afterwards | No routine movement restrictions. Bungee jumping is not allowed. | Usually avoiding bending the hip past 90 degrees or crossing the legs for 6 weeks, to reduce the risk of dislocation |
| Long-term results | A slightly lower re-operation rate on the Australian registry. Read this with caution: in Australia, anterior surgery is more often done by specialist hip surgeons doing larger numbers, which can skew the figures [6] | A slightly higher re-operation rate than the anterior approach on the registry [6] |
| Different risks | Fracture is a more common reason for further surgery [6, 7] | Dislocation is a more common reason for further surgery [6, 7] |
Both the dislocation and fracture risks fall with training and experience. [6, 7]
Surgeon experience. The anterior approach takes time to learn. Australian research found complication rates settle after a surgeon’s first 100 or so anterior hip replacements. [7] Dr Connon trained in the anterior approach under experienced surgeons in Sydney and London, with further training in France and the United States, and now teaches it to orthopaedic registrars and visiting surgeons at Sunshine Coast University Hospital.
“I was fortunate enough to train under some highly experienced anterior approach surgeons in Sydney and London when I was still a trainee surgeon. There was always somebody experienced watching over me, so patients were kept safe throughout the training process.”
Whichever approach is used, a hip replacement relieves pain for most people with advanced arthritis. The main differences are in the first few months.
What about hip resurfacing?
Hip resurfacing caps the ball of the hip rather than replacing it. It’s now uncommon in Australia: 1.5% of hip replacements in 2025, with about half as many operations as at its peak in 2005. Registry data show that in most patients a resurfacing wears out faster than a total hip replacement. [6] It’s still occasionally the best option for a small group of people, and Dr Connon can discuss whether that includes you.
Planning and preparing for surgery
Patient-specific instrumentation. Dr Connon uses patient-specific instrumentation for hip replacement. Your operation is planned from a CT scan of your own hip, and 3D-printed guides and models are made for your hip alone. During surgery, the guides set the size and position of your implants to match the plan.
Once surgery is booked, you’ll usually also see a specialist perioperative physician for a general medical check, attend Joint School (a 2-hour group session with a support person) and go to the hospital’s preadmission clinic. Preparing for joint replacement explains each step, and your joint replacement pathway sets out the whole journey, from referral to recovery.
Anaesthetic. Most people have a spinal anaesthetic, which numbs the lower body during and for a few hours after surgery, combined with a general anaesthetic or light sedation. Dr Connon also injects local anaesthetic around the hip. Your anaesthetist will discuss the options with you.
Hospital stay and recovery
- Day of surgeryUp on your feet a few hours after surgery, and a short walk the same day if your operation is early, with crutches or a four-wheeled walker to help.
- Day 1Walking with help from the hospital physiotherapist, with crutches or a four-wheeled walker.
- Day 1 or 2Home once you’re walking safely with crutches or a walker, can manage stairs and your pain is controlled. Most people stay 1 to 2 nights in hospital; if you’re self-funding, you’ll usually go home on the day of surgery or after 1 night, as long as it’s safe for you and you have support at home.
- 2 to 3 weeksWound check with our nurse practitioner. Stitches dissolve, so there’s nothing to remove.
- 6 to 8 weeksReview with Dr Connon, with an X-ray beforehand. Most people are back to their normal activities around this time.
Inpatient rehabilitation is not usually needed, but it can be arranged if your circumstances require it. For the first 4 weeks, gentle walking is the best exercise. Avoid strenuous physiotherapy until about 4 weeks, when you can reconnect with your community physiotherapist.
Driving once you’re off opioid painkillers: usually about 2 weeks after a left hip replacement (automatic car) and up to 4 weeks after a right. Swimming after about 4 weeks, once your wound has healed. Yoga from about 6 weeks, surfing from about 12 weeks, and golf when your physiotherapist is happy with your strength and stability.
Recovering from hip replacement covers wound care, pain relief and when to call us.
What are the risks?
All surgery carries risks. Dr Connon will discuss them with you, along with your own medical history and medicines, before you decide. Risks include:
- Infection. Uncommon, affecting fewer than 1 in 100 people, [8] but serious. Deep infection can need further operations and long courses of antibiotics. Call us straight away if you’re concerned.
- Fracture of the thigh bone during surgery, more often associated with surgeons early in their learning curve.
- Dislocation. Less common after anterior than posterior approach surgery, but it can still happen.
- Numbness on the outer thigh, from a skin nerve held aside during surgery. The numb area usually shrinks over the following months. It affects feeling, not strength.
- Leg length difference, usually only a few millimetres. A stable hip is the priority, so occasionally a few extra millimetres of length are needed.
- Ongoing pain. Some people still have some pain after a hip replacement.
- Blood loss needing transfusion. Now uncommon in first-time hip replacement. Tell us if you have any objection to blood transfusion.
- Blood clots in the leg (deep vein thrombosis, or DVT) or the lung (pulmonary embolism). You’ll be given blood thinners, calf compression and encouragement to walk.
- Anaesthetic risks, including allergic reactions, heart problems and stroke. These are rare, and your pre-operative medical check helps reduce them.
This list can’t include every possible complication.
How long does a hip replacement last?
Modern hip replacements last much longer than older designs, which used plastics that wore faster. Australian registry data show most modern hip replacements are still working 20 years after surgery, so most people need only one operation on that hip. [6] Further surgery (revision) is more likely in younger, more active people.
What does it cost?
With private health insurance, hip replacement needs Gold hospital cover, or a Silver Plus policy that includes joint replacement. We’ll give you a written quote, including any out-of-pocket costs, before surgery.
Without insurance, a self-funded hip replacement currently costs approximately $27,000 to $28,000 in total, depending on your hospital stay and general health. See self-funded hip and knee replacement.
Common questions
Is there a BMI cut-off for hip replacement?
No. Dr Connon does not have a specific BMI cut-off. Our team will talk with you about optimising the things that affect your recovery, including your HbA1c (a measure of blood sugar control), nutrition, dental health, iron levels, and vitamins C and D. This is discussed at Joint School. See getting your health ready for surgery.
Should I cut down on smoking or alcohol before a hip replacement?
Yes, if you can. Reducing smoking, alcohol and opioid painkillers is strongly recommended, because it improves the speed of your recovery. See getting your health ready for surgery.
How long does the operation take?
The operation itself usually takes about an hour, depending on your anatomy. Allow several hours from admission to returning to the ward, including preparation and recovery from the anaesthetic.
Will I need a raised toilet seat or other hip precautions?
Not usually. The traditional hip precautions apply to the posterior approach. After an anterior hip replacement you can bend, tie your shoes and cross your legs. There are no routine movement restrictions, but bungee jumping is not allowed. Don’t overdo hip-bending exercises in the first 4 weeks.
When can I drive?
Once you’re off opioid painkillers: usually about 2 weeks after a left hip replacement if you drive an automatic, and up to 4 weeks after a right. Check with our nurse practitioner at your wound review.
Can I have a revision through the anterior approach?
Often, yes. Dr Connon performs many revision hip replacements through the anterior approach. See revision hip replacement.
References
- Connon F, Logishetty K. Approaches for total hip arthroplasty. In: Rodriguez-Merchan EC, Liddle AD, eds. Controversies in Orthopaedic Surgery of the Lower Limb. Springer; 2021:41–52. doi:10.1007/978-3-030-80695-8_4
- Miller LE, Gondusky JS, Bhattacharyya S, et al. Does surgical approach affect outcomes in total hip arthroplasty through 90 days of follow-up? A systematic review with meta-analysis. J Arthroplasty. 2018;33(4):1296–1302. doi:10.1016/j.arth.2017.11.011
- Nam D, Nunley RM, Clohisy JC, et al. Does patient-reported perception of pain differ based on surgical approach in total hip arthroplasty? Bone Joint J. 2019;101-B(6 Suppl B):31–36. doi:10.1302/0301-620X.101B6.BJJ-2018-1575.R1
- Barrett WP, Turner SE, Leopold JP. Prospective randomized study of direct anterior vs postero-lateral approach for total hip arthroplasty. J Arthroplasty. 2013;28(9):1634–1638. doi:10.1016/j.arth.2013.01.034
- Parvizi J, Restrepo C, Maltenfort MG. Total hip arthroplasty performed through direct anterior approach provides superior early outcome: results of a randomized, prospective study. Orthop Clin North Am. 2016;47(3):497–504. doi:10.1016/j.ocl.2016.03.003
- Australian Orthopaedic Association National Joint Replacement Registry. Hip, Knee and Shoulder Arthroplasty: 2026 Annual Report. Adelaide: AOA; 2026. registry.aoa.org.au
- de Steiger RN, Lorimer M, Solomon M. What is the learning curve for the anterior approach for total hip arthroplasty? Clin Orthop Relat Res. 2015;473(12):3860–3866. doi:10.1007/s11999-015-4565-6
- Kurtz SM, Lau E, Schmier J, et al. Infection burden for hip and knee arthroplasty in the United States. J Arthroplasty. 2008;23(7):984–991. doi:10.1016/j.arth.2007.10.017
This page is general information based on Dr Frank Connon’s patient information. It isn’t a substitute for advice about your own situation. All surgery carries risks, and outcomes vary between people.
Related
Preparing for hip or knee replacement
Your appointments before joint replacement, Joint School, medicines, the 2 weeks before surgery, fasting and Sip Til Send, and what to pack for hospital.
How to prepareRecovering from hip replacement
What to expect after an anterior hip replacement with Dr Frank Connon: swelling, pain relief, wound care, exercise, driving and activities, and when to call.
Read the recovery guideFees and the cost of surgery
Consultation fees and Medicare rebates, the private health cover you need for joint replacement, and the cost of a self-funded hip or knee replacement.
See fees and costsMake an appointment
Ready to talk about your hip or knee?
Ask your GP for a referral to Dr Frank Connon, or book our nurse practitioner without one. We’ll find a time at whichever rooms suit you.
- Phone
- 07 5413 4300
- Fax
- 07 5238 8022
- Office hours
- Monday to Friday, 9am to 4.30pm
Closed on public holidays. We aim to return voicemails the same business day.